You’re scheduled for a medical procedure, and the anesthesiologist has just explained the plan. You’ll be receiving anesthesia, and they might mention terms like “paralysis” or “unconsciousness.” It’s easy for these to blur together, but understanding the distinction is crucial for your peace of mind and for appreciating the marvel of modern medicine. While both states aim to make you comfortable and immobile during surgery, they achieve this through fundamentally different mechanisms and have distinct implications.
This article will guide you through the nuanced differences between paralysis and unconsciousness in the context of anesthesia. You’ll gain clarity on how each state is induced, what sensations you might experience (or not experience), and why anesthesiologists choose one approach over another.
When we talk about anesthesia, it’s rarely a single switch being flipped. Instead, think of it as a spectrum of interventions designed to manage pain, anxiety, and movement during medical procedures. The anesthesiologist is your navigator on this spectrum, carefully selecting the agents and techniques to best suit your needs and the demands of the surgery.
General Anesthesia: The Complete Immersion
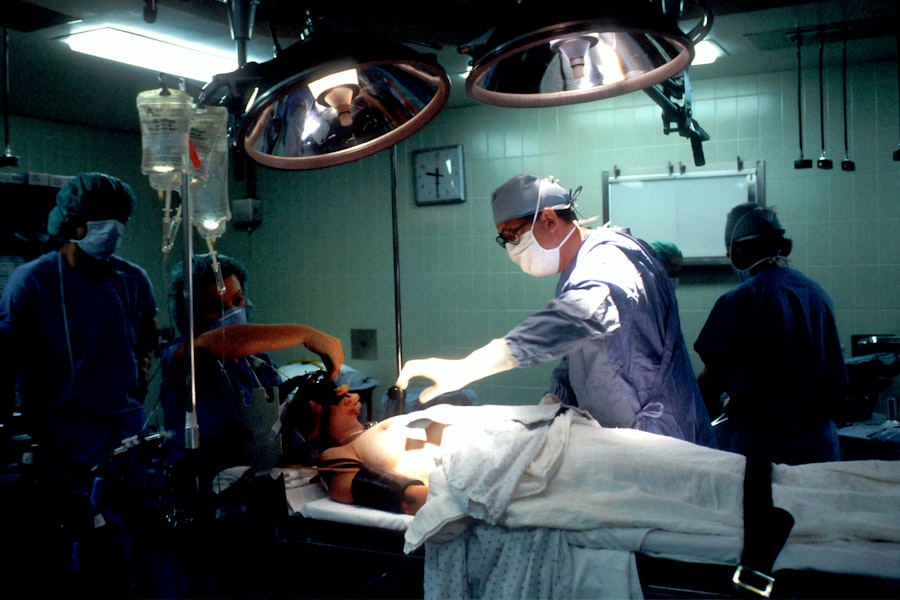
General anesthesia is perhaps what most people envision when they hear the word “anesthesia.” It’s the most profound form of anesthesia, aiming to render you completely unaware of your surroundings, insensible to pain, and immobile. This is achieved through a carefully orchestrated combination of medications, often including intravenous agents and inhaled gases.
Inducing Unconsciousness: The Gateway to General Anesthesia
The primary goal of general anesthesia is to achieve unconsciousness. This is typically induced rapidly, often with an intravenous medication like propofol or etomidate. You’ll feel a sense of drowsiness, and within moments, you’ll drift off to sleep. The anesthesiologist will be constantly monitoring your vital signs – heart rate, blood pressure, oxygen saturation, and breathing – to ensure your safety.
The Role of Sedatives and Hypnotics
Sedatives and hypnotics are the cornerstone of inducing unconsciousness. They work by interacting with specific receptors in your brain, primarily the GABA (gamma-aminobutyric acid) receptors. GABA is an inhibitory neurotransmitter, meaning it reduces nerve activity. By enhancing the effects of GABA, these anesthetic agents effectively dampen the signaling in your brain, leading to a state of profound sedation and eventual unconsciousness.
Beyond Sedation: Amnesia and Analgesia
General anesthesia isn’t just about making you sleep. It also provides amnesia, meaning you won’t remember anything that happened while you were under its effects. Furthermore, it offers potent analgesia, which is pain relief. This is achieved through a combination of the same sedative agents and often supplemented with other medications like opioids.
The Paralytic Component: Facilitating Surgical Access
While unconsciousness is the primary aim for patient comfort, many general anesthetics also induce paralysis. This is not always an intentional or primary goal of the anesthetic itself, but rather a common side effect of the potent agents used or a specifically administered medication to achieve a crucial surgical objective.
Muscle Relaxants: The Tools of Immobilization
To achieve surgical paralysis, anesthesiologists often administer neuromuscular blocking agents, commonly known as muscle relaxants. These drugs work by blocking the transmission of nerve signals at the neuromuscular junction – the point where nerves communicate with muscles. Without these signals, your muscles cannot contract, leading to a state of flaccid paralysis.
Depolarizing vs. Non-depolarizing Blockers
There are two main classes of neuromuscular blocking agents: depolarizing and non-depolarizing.
Depolarizing blockers, such as succinylcholine, work by mimicking acetylcholine, the neurotransmitter that causes muscle contraction. They bind to acetylcholine receptors at the neuromuscular junction, causing a prolonged depolarization of the muscle membrane. This initial depolarization can lead to brief muscle fasciculations (twitches) before the muscle becomes unable to respond to further stimulation and becomes paralyzed. The duration of action for depolarizing blockers is typically short.
Non-depolarizing blockers, like rocuronium or vecuronium, work by competitively blocking acetylcholine from binding to its receptors. They essentially occupy the receptors, preventing the muscle from receiving the signal to contract. These agents generally have a longer duration of action than depolarizing blockers and their effects can be reversed with specific medications.
Why Induce Paralysis? Beyond Patient Comfort
While you are unconscious and therefore not directly experiencing discomfort from muscle activity, paralysis is a critical component for successful surgery in many cases.
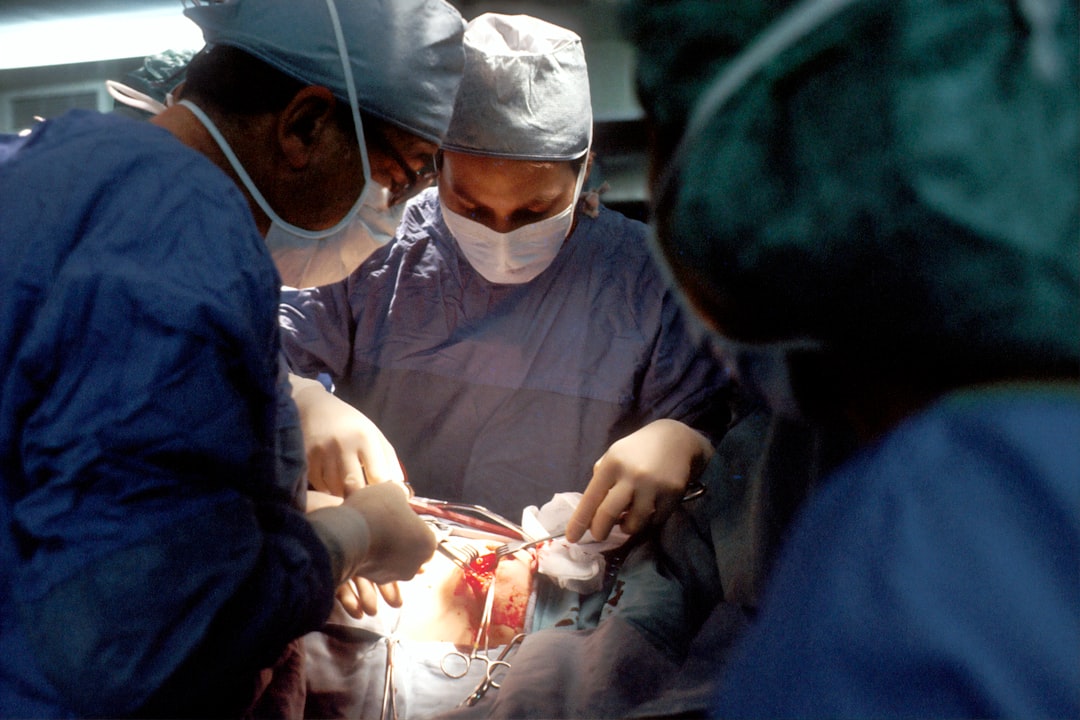
- Optimal Surgical Field: Many surgical procedures, especially those in the abdominal cavity or chest, require the surgeon to have a completely still and relaxed operative site. Muscle relaxants ensure that abdominal organs don’t shift, that the diaphragm doesn’t interfere with breathing, and that there’s no involuntary movement from the patient. This allows for precise dissection and reduces the risk of accidental injury.
- Facilitating Endotracheal Intubation: For most general anesthetics, an endotracheal tube is inserted into the trachea to secure an airway and allow for controlled mechanical ventilation. Muscle relaxants are essential for relaxing the muscles of the jaw and pharynx, making the intubation process smoother and less traumatic for the patient and the anesthesiologist.
- Reducing Physiological Stress: In certain surgeries, intense muscle activity can lead to significant physiological stress, including increased heart rate and blood pressure. Paralysis can help mitigate these responses, making the patient’s physiological state more stable.
In the discussion of anesthesia, it is crucial to differentiate between paralysis and unconsciousness, as both states can significantly impact patient safety and outcomes. A related article that delves into these concepts is available at Freaky Science, where the complexities of anesthesia are explored in detail. Understanding how these two states interact can help medical professionals provide better care and ensure that patients are well-informed about their experiences during surgical procedures.
Local and Regional Anesthesia: Targeted Numbness
In contrast to general anesthesia, local and regional anesthesia aim to numb a specific area of the body, blocking pain sensation while the patient remains conscious or sedated. Here, the focus is on preventing the transmission of pain signals, not necessarily on inducing unconsciousness or widespread muscle paralysis.
Local Anesthesia: The Small-Scale Solution
Local anesthesia involves injecting a numbing medication directly into the tissue at the site of the procedure. This is commonly used for minor surgeries, dental work, or when a small area needs to be desensitized.
How Local Anesthetics Work
Local anesthetics, such as lidocaine or bupivacaine, work by blocking sodium channels in nerve cells. Sodium channels are essential for the propagation of nerve impulses. By preventing sodium from entering the nerve cell, local anesthetics effectively stop the nerve from sending pain signals to the brain.
Mechanism of Sodium Channel Blockade
When a nerve is stimulated, there’s a rapid influx of sodium ions into the nerve cell, causing depolarization and the generation of an action potential (nerve impulse). Local anesthetics, in their charged form, bind to the inner pore of the voltage-gated sodium channel when it is in its open or inactivated state. This binding physically obstructs the passage of sodium ions, thereby preventing depolarization and the transmission of the nerve impulse.
Consciousness and Paralysis: Minimal Impact
With local anesthesia, you typically remain fully conscious. You might be offered some mild sedation to help you relax, but you are aware of your surroundings. There is no generalized paralysis. The anesthetic only affects the nerves in the immediate area of injection. You will be able to move the parts of your body that are not anesthetized.
Regional Anesthesia: Numbing Larger Areas
Regional anesthesia takes local anesthesia a step further, targeting a larger area of the body by blocking nerve bundles or nerve roots. This can involve techniques like spinal anesthesia, epidural anesthesia, or nerve blocks.
Spinal and Epidural Anesthesia: Lower Body Focus
Spinal and epidural anesthesia are commonly used for procedures involving the lower body, such as childbirth, hip surgery, or knee surgery.
Spinal Anesthesia: A small amount of local anesthetic is injected directly into the cerebrospinal fluid within the subarachnoid space in your lower back. This bathes the spinal cord and blocks nerve signals from the lower half of your body. The onset is rapid, and the block is dense, providing profound numbness and often some degree of motor block (weakness or inability to move the legs).
Epidural Anesthesia: An anesthetic is injected into the epidural space, which is outside the dura mater (the membrane surrounding the spinal cord). This can be done with a continuous catheter, allowing for prolonged pain relief and adjustable levels of anesthesia. Epidurals can provide significant pain relief during labor while still allowing for some movement.
Peripheral Nerve Blocks: Precision Targeting
Peripheral nerve blocks involve injecting local anesthetic near specific nerves or nerve plexuses (clusters of nerves) that supply a particular limb or region. This is often used for surgeries on the arm, leg, or hand.
- Upper Extremity Blocks: These can numb the entire arm, from the shoulder to the fingertips, allowing for procedures like carpal tunnel surgery or shoulder surgery.
- Lower Extremity Blocks: These can numb the leg for procedures like foot surgery or knee surgery.
The Balance of Sensation and Motor Function
In regional anesthesia, the anesthesiologist carefully calibrates the dose and type of anesthetic to achieve the desired level of pain relief while potentially preserving some motor function, depending on the procedure. You might experience a significant reduction in sensation and a feeling of heaviness or weakness in the anesthetized area, but this is a localized effect, not a systemic paralysis.
The Nuance of “Paralysis” in Anesthesia
The word “paralysis” can be a loaded term. In the context of anesthesia, it’s crucial to understand that it doesn’t always mean the complete inability to move any muscle in your body. The depth and extent of paralysis are carefully controlled.
Motor Blockade: A Spectrum of Weakness
When muscle relaxants are used during general anesthesia, they induce a motor blockade. This blockade can range from subtle weakness to complete flaccid paralysis. The anesthesiologist uses nerve stimulators to assess the level of blockade, ensuring it’s sufficient for surgery but also allowing for timely reversal at the end of the procedure.
Assessing the Depth of Blockade
Nerve stimulators are small devices that deliver a mild electrical current to a peripheral nerve. This elicits a muscle response, which can be observed or measured. By applying different patterns of stimulation (e.g., single twitch, train-of-four), the anesthesiologist can quantify the degree of neuromuscular blockade. A complete block means no muscle response is detected, while a partial block indicates some residual muscle function.
Reversal of Neuromuscular Blockade
At the end of surgery, once the anesthesiologist has achieved adequate hemostasis and the surgical stimulation has ceased, the effects of the muscle relaxants need to be reversed. This is typically done using specific medications that counteract the action of the neuromuscular blocking agents. For non-depolarizing blockers, agents like neostigmine or sugammadex are used to restore neuromuscular function. The goal is for you to regain normal muscle strength and the ability to breathe on your own before you wake up.
Voluntary Movement vs. Reflex Activity
It’s important to remember that even with a significant motor block, some reflexive muscle activity might persist. However, voluntary, coordinated movement is typically suppressed. You will not be able to consciously move your limbs in a purposeful way when under the influence of sufficient muscle relaxants.
Unconsciousness: The Absence of Awareness
Unconsciousness, in the context of anesthesia, is the profound state of not being aware of your surroundings. It’s the absence of wakefulness and the inability to perceive pain, stimuli, or events.
The Brain Under Anesthesia: Altered States of Consciousness
Anesthetic agents profoundly alter brain activity. They disrupt the communication between different parts of the brain and interfere with the neural networks responsible for consciousness, memory, and sensory processing.
Neurotransmitter Systems Involved
As mentioned earlier, GABA receptors are central to the action of many anesthetic agents. However, other neurotransmitter systems are also involved, including:
- Glutamate receptors: These are excitatory receptors, and anesthetics often inhibit their function, reducing overall brain excitation.
- Serotonin and Norepinephrine systems: These systems are involved in wakefulness and arousal, and anesthetics can depress their activity.
- Acetylcholine receptors: These play a role in learning and memory, and their blockade contributes to the amnesic effects of anesthesia.
The complex interplay of these neurotransmitter systems leads to the reversible loss of consciousness.
The Goal of Unconsciousness: Patient Safety and Comfort
The primary reason for inducing unconsciousness during general anesthesia is to ensure your absolute comfort and safety. You are unable to experience pain, distress, or anxiety. It also prevents you from moving involuntarily, which could interfere with the surgical procedure and potentially cause harm.
Distinguishing from Sleep
While general anesthesia can resemble deep sleep, it’s a medically induced state with specific physiological goals. You can’t be easily roused from general anesthesia by external stimuli, unlike natural sleep.
Understanding the differences between paralysis and unconsciousness during anesthesia is crucial for both medical professionals and patients. A related article that delves deeper into this topic can be found at Freaky Science, where it explores the mechanisms of anesthesia and the implications for patient safety. This resource provides valuable insights into how anesthetics affect the body and mind, helping to clarify common misconceptions surrounding these states.
When Is Which Used? The Art of Anesthetic Choice
The decision to use general anesthesia with paralysis, or regional/local anesthesia with or without sedation, is a complex one that depends on numerous factors. The anesthesiologist will consider the type and duration of the surgery, your overall health, your preferences, and potential risks.
General Anesthesia: For Complex or Invasive Procedures
General anesthesia is often the preferred choice for:
- Extensive or long surgeries: When the procedure is expected to be lengthy or involve significant manipulation of internal organs.
- Surgeries involving the head, neck, or chest: These areas require precise control and immobility.
- Patients who are unable to tolerate regional anesthesia: Due to anatomical challenges or patient anxiety.
- Emergency surgeries: When rapid induction of unconsciousness is necessary.
Regional and Local Anesthesia: For Targeted Interventions
Regional and local anesthesia are favored for:
- Shorter procedures on limbs or the lower body: When a localized area can be effectively numbed.
- Patients with significant underlying health conditions: As they generally carry fewer systemic risks than general anesthesia.
- Pain management during labor and delivery: Epidurals are a prime example.
- Post-operative pain control: Nerve blocks can provide significant pain relief after surgery, reducing the need for opioids.
The Role of Sedation in Regional Anesthesia
While regional anesthesia primarily focuses on blocking pain, it’s often combined with sedation to enhance patient comfort and reduce anxiety. This sedation can range from minimal (making you drowsy) to moderate (making you sleepy but still responsive). In these cases, you are not unconscious in the same way you would be under general anesthesia.
Conclusion: The Marvel of Controlled States
Understanding the differences between paralysis and unconsciousness in anesthesia demystifies a vital aspect of modern medicine. You now appreciate that “paralysis” in this context refers to the controlled relaxation of muscles to facilitate surgery, while “unconsciousness” is the absence of awareness for your comfort and safety. Both are powerful tools wielded by skilled anesthesiologists to ensure your well-being during medical procedures.
The anesthesiologist’s expertise lies in precisely controlling these states, tailoring the anesthetic plan to your individual needs. Whether you drift into a dreamless sleep or remain awake and comfortable while a specific part of your body is numbed, the goal remains the same: a safe and successful outcome for your medical journey. The next time you hear these terms, you’ll have a clearer understanding of the incredible science at play.

You’re Not Asleep Under Anesthesia. So Where Do You Go?
FAQs
What is the difference between paralysis and unconsciousness during anesthesia?
Paralysis refers to the inability to move or feel sensation, while unconsciousness refers to the lack of awareness or perception. During anesthesia, paralysis is induced to prevent movement during surgery, while unconsciousness is induced to prevent the patient from feeling pain or being aware of the procedure.
How is paralysis achieved during anesthesia?
Paralysis during anesthesia is achieved through the use of neuromuscular blocking agents, which temporarily block the transmission of nerve impulses to the muscles, resulting in paralysis. This allows the surgical team to perform the procedure without the patient moving.
How is unconsciousness achieved during anesthesia?
Unconsciousness during anesthesia is achieved through the use of anesthetic agents, which act on the brain to induce a state of unconsciousness. These agents can be administered through inhalation or intravenous injection.
Are paralysis and unconsciousness always induced together during anesthesia?
No, paralysis and unconsciousness are not always induced together during anesthesia. In some cases, such as regional anesthesia or certain types of surgery, only unconsciousness may be required, while in other cases, such as certain types of spinal surgery, paralysis may be induced without unconsciousness.
What are the potential risks and complications of paralysis and unconsciousness during anesthesia?
The potential risks and complications of paralysis and unconsciousness during anesthesia include respiratory depression, awareness under anesthesia, and postoperative muscle weakness. It is important for the anesthesia team to carefully monitor and manage these effects to ensure the safety and well-being of the patient.